


Anal Fistula
We are here for your care
Anal Fistula Treatment in Mumbai – Surgery, Procedures & Recovery
An anal fistula is a small tunnel that develops between the inside of the anal canal and the skin around the anus. It usually forms after an infection or abscess and rarely heals on its own – surgery is almost always required for a complete cure.
Dr. Husain Gheewala is a Colorectal Surgeon in Mumbai with over a decade of specialist experience in treating anal fistulas, including complex and recurrent cases. Trained at York NHS Hospital (UK) and Severance Hospital (South Korea), he performs sphincter-preserving fistula procedures across Saifee Hospital, Wockhardt, Apollo Spectra, Masina, and other leading South Mumbai hospitals.

What Is an Anal Fistula?
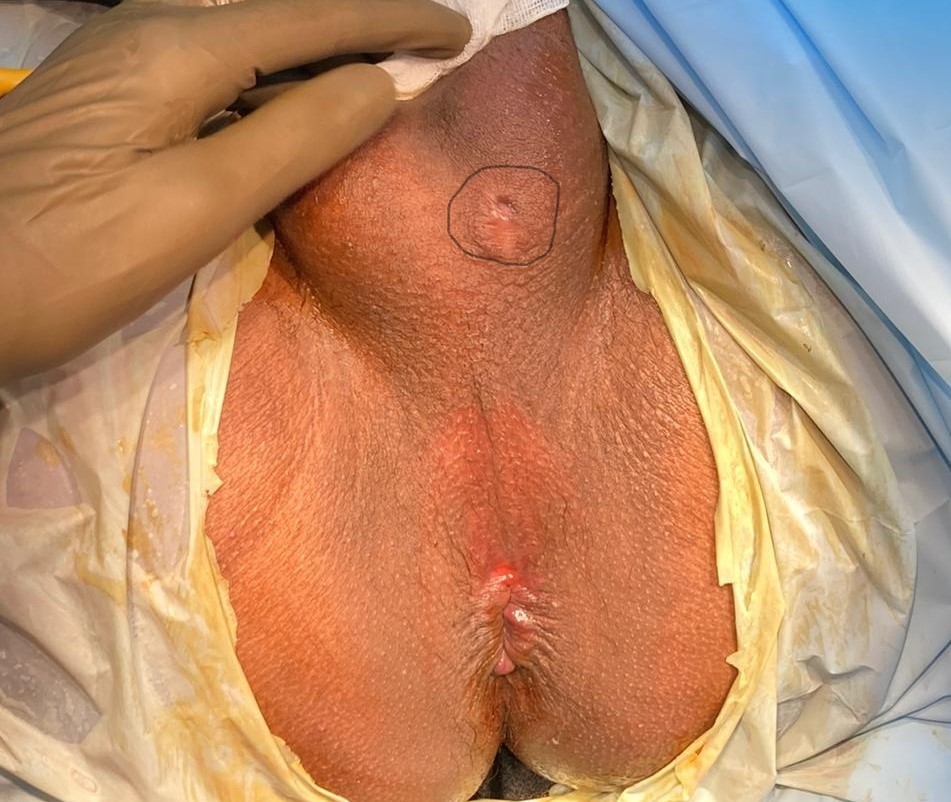
An anal fistula is an abnormal channel that connects an infected gland inside the anal canal to an opening on the skin near the anus. The tunnel itself is the fistula.
Most fistulas begin as a perianal abscess – a painful collection of pus near the anus. When the abscess drains (either on its own or through a procedure), the channel left behind can persist as a fistula. About 40% of patients who develop an anal abscess go on to form a fistula, regardless of how the abscess was treated.
Fistulas can be simple (a single short tract) or complex (multiple branches, high tracts that cross sphincter muscle, or tracts associated with Crohn’s disease). The complexity of the fistula determines which surgical procedure is appropriate.
Causes
The lifetime risk of developing an anal fistula is about 1 in 1000. The disease tends to me more common in men, and the most common age group is 20-50.
Often it is young and otherwise healthy people who develop an anal fistula, and in most cases, it is due to bad luck. The disease has nothing to do with hygiene. The only known risk factor is cigarette smoking, although many people who develop the disease are non-smokers.
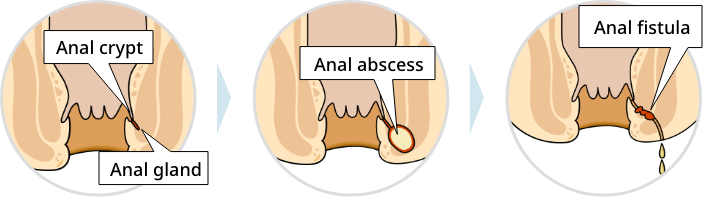
We are all born with tiny glands within the anal canal, only about 1-2cm inside the anal opening. There are usually 10-20 of these oil glands; their function is thought to be related to lubrication of the anal canal to facilitate defecation.
Just like oil glands on the face, these glands can sometimes become blocked with thick secretions and then subsequently get infected.
When this happens, an abscess occurs, and pus from the abscess will follow the path of least resistance. The abscess will track under, in between, or through the adjacent anal sphincter muscle. Sometimes the abscess will travel into the fat around the anus.
Of all patients who develop one of these abscesses, about 40% will go on to develop a fistula, regardless of what treatment is given to them at the time of the abscess. The fistula will occur between where the infection started, within the anal canal, and where the abscess drained to on the outside of the anus.
Causes & Risk Factors
Most anal fistulas develop because of infected anal glands. We all have 10–20 small oil glands inside the anal canal that lubricate stool passage. When one of these glands gets blocked, bacteria can multiply and cause an abscess. As the infection tracks outwards, it forms the fistula channel.
Anal fistulas are not caused by poor hygiene. The lifetime risk is roughly 1 in 1,000, with men aged 20–50 most commonly affected. Other contributing conditions include:
- Crohn’s disease and other inflammatory bowel diseases
- Previous anorectal surgery or trauma
- Tuberculosis or HIV-related infections
- Radiotherapy to the pelvic area
- Hidradenitis suppurativa (a chronic skin condition)
- Diverticulitis affecting nearby structures
Symptoms – When to See a Specialist
Anal fistula symptoms often come and go, which is one reason patients delay seeking care. Common symptoms include:
- Persistent or intermittent pus, blood, or fluid discharge from a small opening near the anus
- Throbbing pain around the anus that may worsen on sitting, walking, or passing stool
- Skin irritation, itching, or redness around the anal opening
- A small lump or bump near the anus that fills with pus and drains repeatedly
- Fever or feeling generally unwell during active infection
- In some cases, difficulty controlling bowel movements
If any of these symptoms persist for more than a few days, or if they recur after a period of relief, you should consult a colorectal specialist. Early assessment significantly improves outcomes and reduces the risk of the fistula becoming more complex.

When to get an advice?
It is important that some one with fistula should be treated by an experienced colorectal surgeon.
The aim should be complete cure by removing the entire tract, whilst at the same time preserving normal anorectal function.
Clinical examination, along with a detailed history provides most of the information. Further tests to confirm the diagnosis and determine the most suitable treatment may be needed.
These may include:
- a further physical and rectal examination
- a proctoscopy, where a special telescope with a light on the end is used to look inside your anus
- an Ultrasound scan, MRI Scan or CT scan.
Treatment
Anal fistulas usually require surgery as they rarely heal if left untreated.
Once you have been assessed and diagnosed with an anal fistula, your colorectal surgeon will advise you on what treatment options there are. The aim is to cure the anal fistula, but at the same time preserve normal anorectal function.
There are many types of operations to choose from for anal fistulae. The main problems with all these operations are that none of them are able to provide a 100% guarantee of success and healing of the fistula, with no risk to normal continence and function of the anus. Hence it is important that you consult an experienced Colorectal surgeon who will guide you for cure. Dr. Husain Gheewala has performed hundreds of such operation and cured complex Anal Fistulas.

How Anal Fistula Is Diagnosed
Accurate diagnosis is essential because the surgical approach depends entirely on mapping the fistula tract – how it runs, how much sphincter muscle it crosses, and whether there are any branches or hidden collections of infection.
Dr. Gheewala’s diagnostic workflow includes:
- Clinical examination – visual inspection of the perianal area and digital rectal examination.
- Proctoscopy – a short, lit telescope used to examine the anal canal and identify the internal opening of the fistula.
- MRI Fistulogram – the gold standard imaging test for complex fistulas. MRI shows the full tract, any branches, and any undrained collections of infection. This is especially important before surgery for high or recurrent fistulas.
- Examination Under Anaesthesia (EUA) – in some cases the fistula is mapped in the operating theatre under anaesthesia so that the surgeon can fully assess the tract before deciding the definitive procedure.
- Endoanal ultrasound or CT scan – used selectively when MRI is not feasible or further information is needed.
Treatment Options for Anal Fistula
Anal fistulas almost always need surgery. The goal of every procedure is the same: completely remove or close the infected tract while preserving normal anal function and bowel control. The choice of procedure depends on how complex the fistula is and how much sphincter muscle it involves.
Dr. Gheewala – Robotic surgeon in mumbai performs the four conventional, evidence-based fistula procedures used internationally:
Choosing the Right Procedure
There is no single best fistula surgery – the right procedure depends on your individual anatomy. Key factors include:
- How much sphincter muscle the tract crosses
- Whether the fistula is simple, complex, or recurrent
- Whether active infection is still present
- Whether you have had previous fistula surgery
- Whether there is underlying Crohn’s disease or other inflammatory condition
In many complex cases, treatment is staged – a seton is placed first to control infection and mature the tract, followed weeks or months later by a LIFT or advancement flap to close the fistula. This staged approach gives the best balance of cure and continence preservation.
Recovery After Anal Fistula Surgery
Most fistula procedures are performed as day care or with a short hospital stay. Recovery depends on the procedure and the complexity of the fistula, but general guidance is:
- Pain is usually well controlled with oral medication for the first few days.
- Sitz baths (sitting in warm water) 2–3 times a day help keep the wound clean and reduce discomfort.
- Most patients can return to desk-based work within a week to ten days.
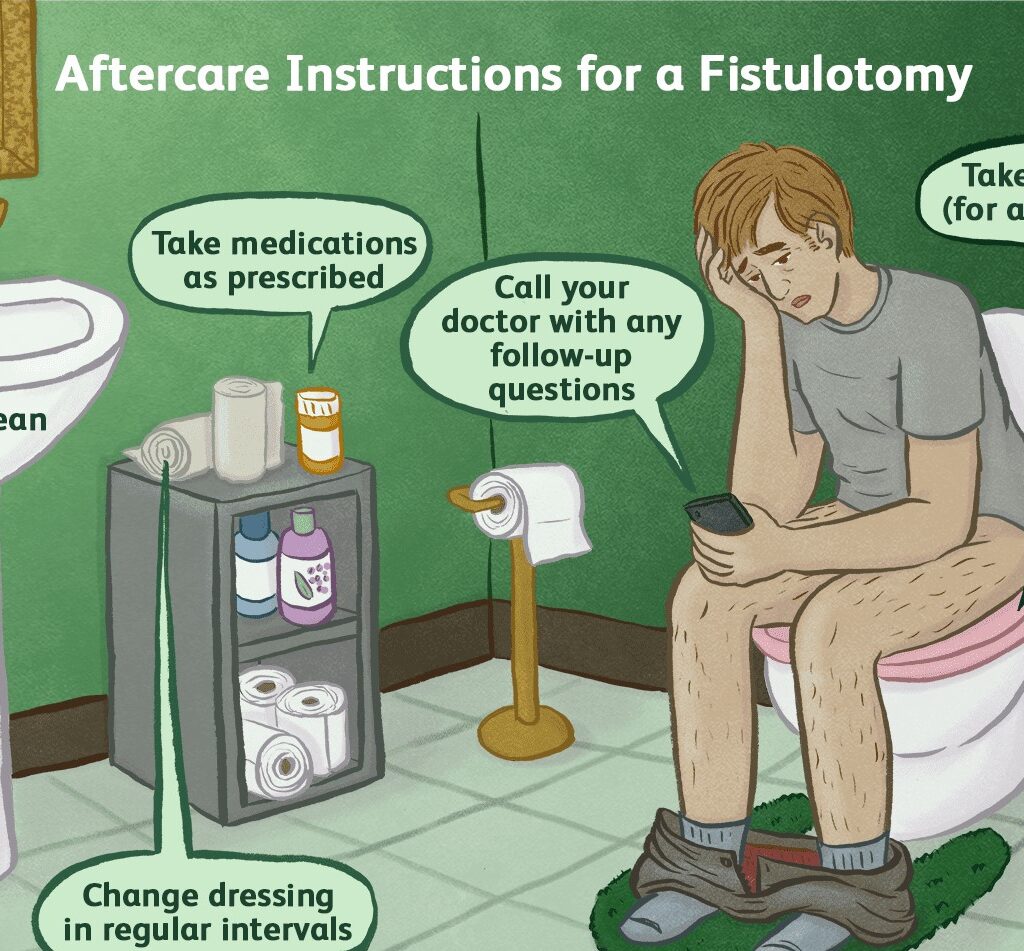
- Wound dressings need regular changing – instructions and follow-up visits are scheduled with Dr. Gheewala.
- A high-fibre diet and adequate water intake prevent constipation, which is critical for healing.
- Full healing of an open fistulotomy wound can take 6–8 weeks; sphincter-preserving procedures heal faster.
Follow-up visits are essential. Most fistula recurrences happen within the first six months after surgery, and early review allows any issue to be caught and addressed before it becomes a larger problem.
Why Choose Dr. Husain Gheewala
Anal fistula surgery is highly technique-dependent. The right procedure performed by an experienced colorectal surgeon offers a high chance of cure with preserved continence. The wrong procedure – or the right procedure performed without proper assessment – can lead to recurrence or incontinence.
- MBBS, MIMER Medical College, Pune
- MRCS – Royal College of Surgeons, Edinburgh, UK
- Two-year Colorectal Surgery Fellowship – York NHS Hospital, UK
- Robotic Surgery training – Severance Yonsei Hospital, Seoul, South Korea
- Hundreds of fistula procedures performed, including complex and recurrent cases
- Affiliated with Saifee Hospital, Wockhardt (Mumbai Central), Masina, Noor, Cumballa Hill, Apollo Spectra (Tardeo), Elizabeth, and Conwest Manjula Badani Jain Hospitals